Cancer proteomics projects often need relative protein ratios across tumor and reference samples, treatment arms, or stage groups that can be labeled into one tandem mass tag (TMT) plex. TMT-based quantitative proteomics tags peptides from each channel, mixes them, and reads reporter-ion intensities after fragmentation so predefined cancer contrasts share one liquid chromatography-tandem mass spectrometry (LC-MS/MS) path (Thompson et al. 2003). The useful application question is whether the cancer sample set can freeze at labeling, not whether cancer biology is complex. Transcript profiles do not substitute for protein ratios; TMT also does not convert reporter ratios into clinical diagnosis or treatment selection.
TMT cancer applications are relative by default. Amount or concentration on named peptides needs a matched stable isotope-labeled internal standard (SIS) and a targeted follow-up design. Co-isolated precursors at MS2 can compress true fold changes; an additional MS3 reporter scan can reduce that mixing on compatible instruments (Ting et al. 2011). It does not repair unmatched protein input or incomplete labeling.
In MtoZ Biolabs quantitative offerings, TMT cancer projects are scoped when experimental groups, replicates, and a relative contrast are declared before tagging. Service intake appears in TMT Quantitative Proteomics Analysis Service.
What TMT Application Covers in Cancer Proteomics Projects
Four application layers belong in the brief and stay separated.
Design layer maps tumor, adjacent, stage, treatment, or subtype arms onto TMT channels, including biological replicates and any bridge channel across plexes.
Sample layer matches extraction, digestion, and protein load across arms so channel offsets are less likely to be read as biology.
Detection layer identifies peptides and records reporters at MS2 or MS3 after labeling, pooling, and optional fractionation.
Claim layer states relative protein change for the frozen cancer contrast. Biomarker candidate listing, pathway triage, or drug-response ranking still need separate validation before diagnostic or therapeutic language.
TMT cancer application remeasures relative ratios inside a freezable plex. It does not invent clinical cutoffs from an unlabeled discovery theme.
Cancer Study Designs Where TMT Multiplexing Fits
TMT fits cancer designs that can name every harvest before quenching and mixing.
Tumor-versus-adjacent or tumor-versus-matched normal sets fit when matrix type is comparable and channel layout is written early. Multi-stage or multi-condition panels fit when stages or doses occupy declared tags. Pre- and post-treatment series fit when both time points are available for the same plex, or when a bridge sample links a second plex. Subtype or phenotype panels fit when membership is closed and replicates are balanced across channels.
Those designs share one requirement. The comparison set is known early enough that amines can be labeled and mixed before acquisition. Shared chromatography then removes run-to-run retention-time drift for that mixed set. Open enrollment cohorts that keep adding tumors after mixing usually need unlabeled label-free quantification (LFQ) or data-independent acquisition (DIA) instead. General TMT application framing outside cancer themes appears in Application of TMT Labeling in Quantitative Proteomics Detection.
Microenvironment, immune-cell, or extracellular-vesicle cancer studies can use TMT when the cell or vesicle preparation is matched across arms and the contrast is frozen. They do not become immune-exhaustion or metastasis claims from enrichment language alone.
End-to-End Workflow for a Cancer TMT Project
A practical cancer TMT spine usually runs as follows.
- Freeze cancer contrast, replicates, channel map, and relative versus amount claim before labeling.
- Match tissue or cell harvest, extraction buffer, and protein load across all arms.
- Digest under matched conditions; confirm comparable peptide input before tagging.
- Label each digest with one TMT channel; quench and clean up residual reagents.
- Pool labeled peptides; fractionate when identification depth is required for the claim.
- Acquire LC-MS/MS with declared MS2 or MS3 reporter readout and quality control (QC) injections.
- Search spectra, extract reporters, apply impurity correction, and roll peptides to proteins.
- Test only the predefined cancer contrast; review ratio compression and missingness before pathway language.
- Archive channel map, instrument method, search settings, and software versions with deliverables.
Steps 1 through 3 protect the cancer sample record. Steps 4 through 9 are the labeling, acquisition, and informatics record. Analysis coupling of identification to reporters appears in Principle of TMT-Based Quantitative Proteomics Analysis. When MS2 fold changes look compressed in complex tumor digests, MS3 options appear in TMT MS3 and SPS-MS3: How to Mitigate Ratio Compression and Enhance Quantitative Accuracy.
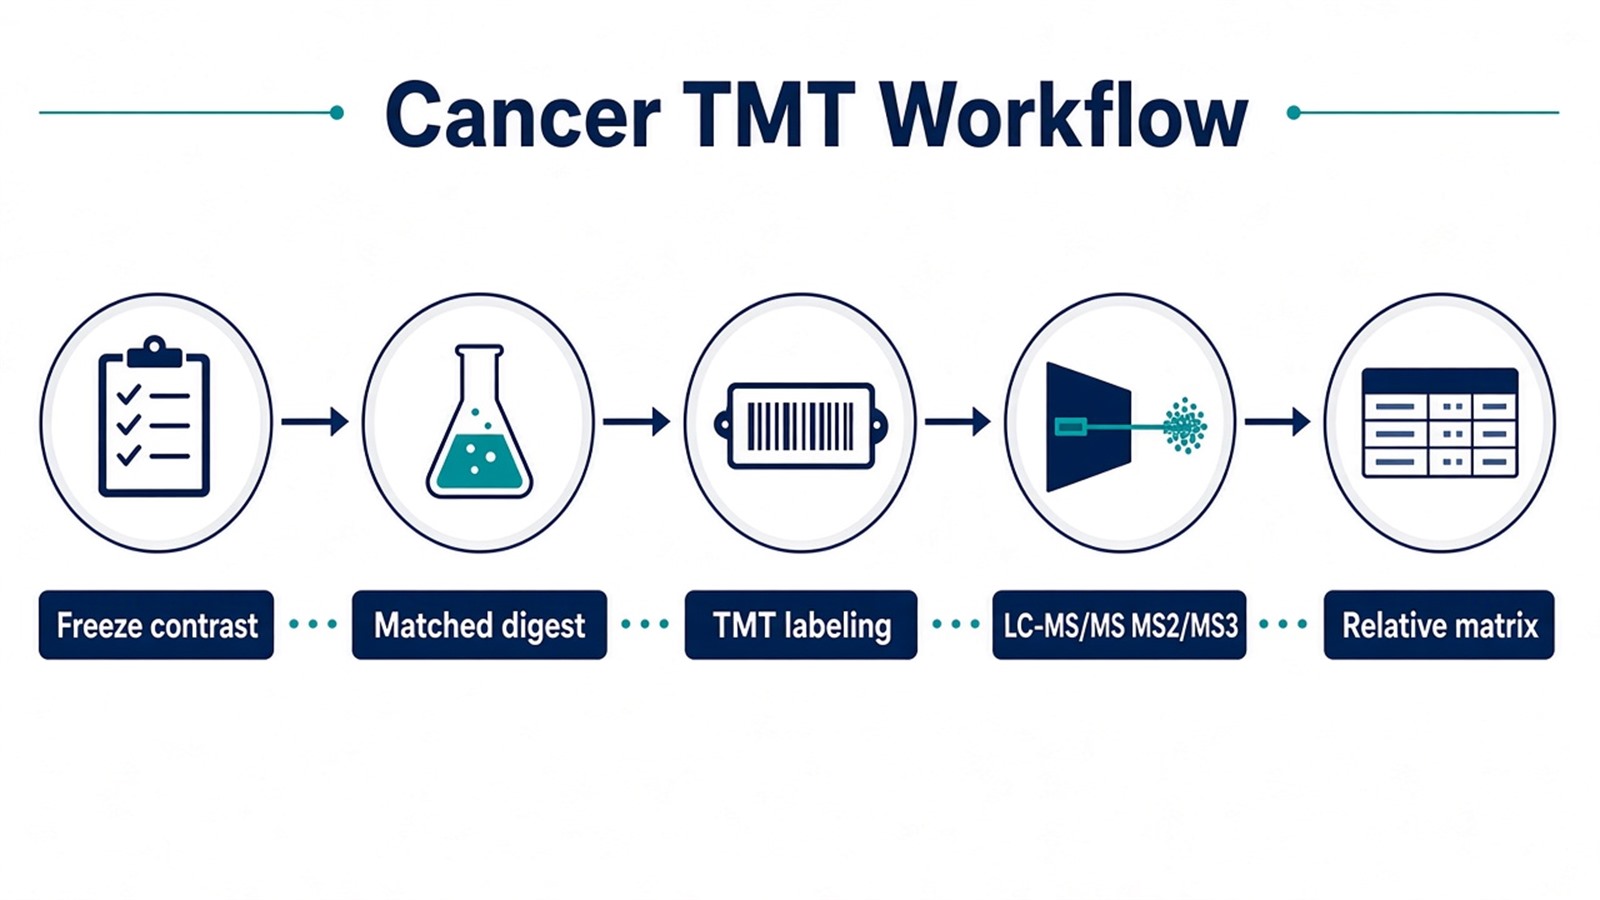
Figure 1. Cancer TMT application depends on a frozen channel map and matched pretreatment before tumor contrasts are tested.
Parameters That Must Be Locked for Cancer TMT Claims
Layer |
Parameter that must be declared |
Failure mode if ignored |
|---|---|---|
Contrast |
Tumor arms and replicates before labeling |
Post hoc regrouping read as biology |
Channel map |
Tag-to-sample layout and bridge plan |
Unlinked plexes treated as one matrix |
Prep |
Matched extraction and digest across arms |
Load or matrix shift as treatment effect |
Labeling |
Completeness checks and quenching |
Incomplete tags as abundance change |
Fractionation |
Depth plan versus instrument time |
Sparse IDs for the intended pathway claim |
Reporter scan |
MS2 or MS3 rule |
Compressed fold changes read as weak biology |
Search |
Database, FDR, unique-peptide rules |
Homolog mixing as subtype signal |
Normalization |
Within-plex assumption stated |
Scale drift as differential biology |
QC |
Pools, blanks, and labeling checks |
Undetected batch or channel failure |
Deliverable |
Matrix, channel map, method notes |
Report rebuilt after acquisition |
Limits follow the same table. Multiplex kit size is a logistics parameter, not a biological result. High coverage language does not replace matched loads. PTM cancer claims need enrichment and modified-peptide search rules declared separately; an unenriched TMT file does not map phosphorylation or acetylation by default.
What a Cancer TMT Result Can Support
A reviewed TMT matrix supports relative comparison of the same protein across channels that were mixed into one plex for a predefined cancer contrast. Pathway enrichment and interaction maps are optional after the ratio matrix passes quality checks. They do not repair unmatched prep or invent diagnostic cutoffs.
Ratio compression can shrink a real tumor-versus-normal or drug-response effect when co-isolation is severe (Ting et al. 2011). A small observed fold change still needs isolation QC before it is called weak biology. Missing reporters do not prove protein absence in a tumor. Shared peptides can pull homologs into one protein group, which matters for subtype language.
Candidate biomarker lists from TMT cancer projects remain research shortlists. Confirmation of named peptides usually needs targeted parallel reaction monitoring (PRM) or multiple reaction monitoring (MRM) in a new digest. Absolute concentration claims need SIS-supported targeted assays, not ordinary TMT reporter tables.
A cancer TMT table supports same-protein relative contrasts inside a locked plex. It does not certify clinical biomarkers or therapy choice.
How to Choose TMT for Cancer Projects Versus Adjacent Routes
Use freezable group structure, matrix match, claim unit, and follow-up need together.
Project need |
Route that often fits |
Recheck before committing |
|---|---|---|
Tumor versus matched reference on a fixed set |
TMT relative plex |
Samples still arriving after mixing |
Multi-stage or multi-dose cancer panel |
Channels mapped before tagging |
Stages added after the plex is mixed |
Open enrollment tumor cohort |
Unlabeled LFQ or DIA |
Force late tumors into an existing TMT mix |
Compressed MS2 ratios in complex digests |
TMT with MS3 review |
Keep MS2 without isolation QC |
Named peptide confirmation |
Targeted PRM or MRM follow-up |
Re-run the same TMT table as confirmation |
Amount or concentration unit |
SIS-supported targeted assay |
Ordinary TMT ratios read as ng per mL |
PTM signaling claim |
Enrichment plus declared modified search |
Unenriched TMT file as phospho map |
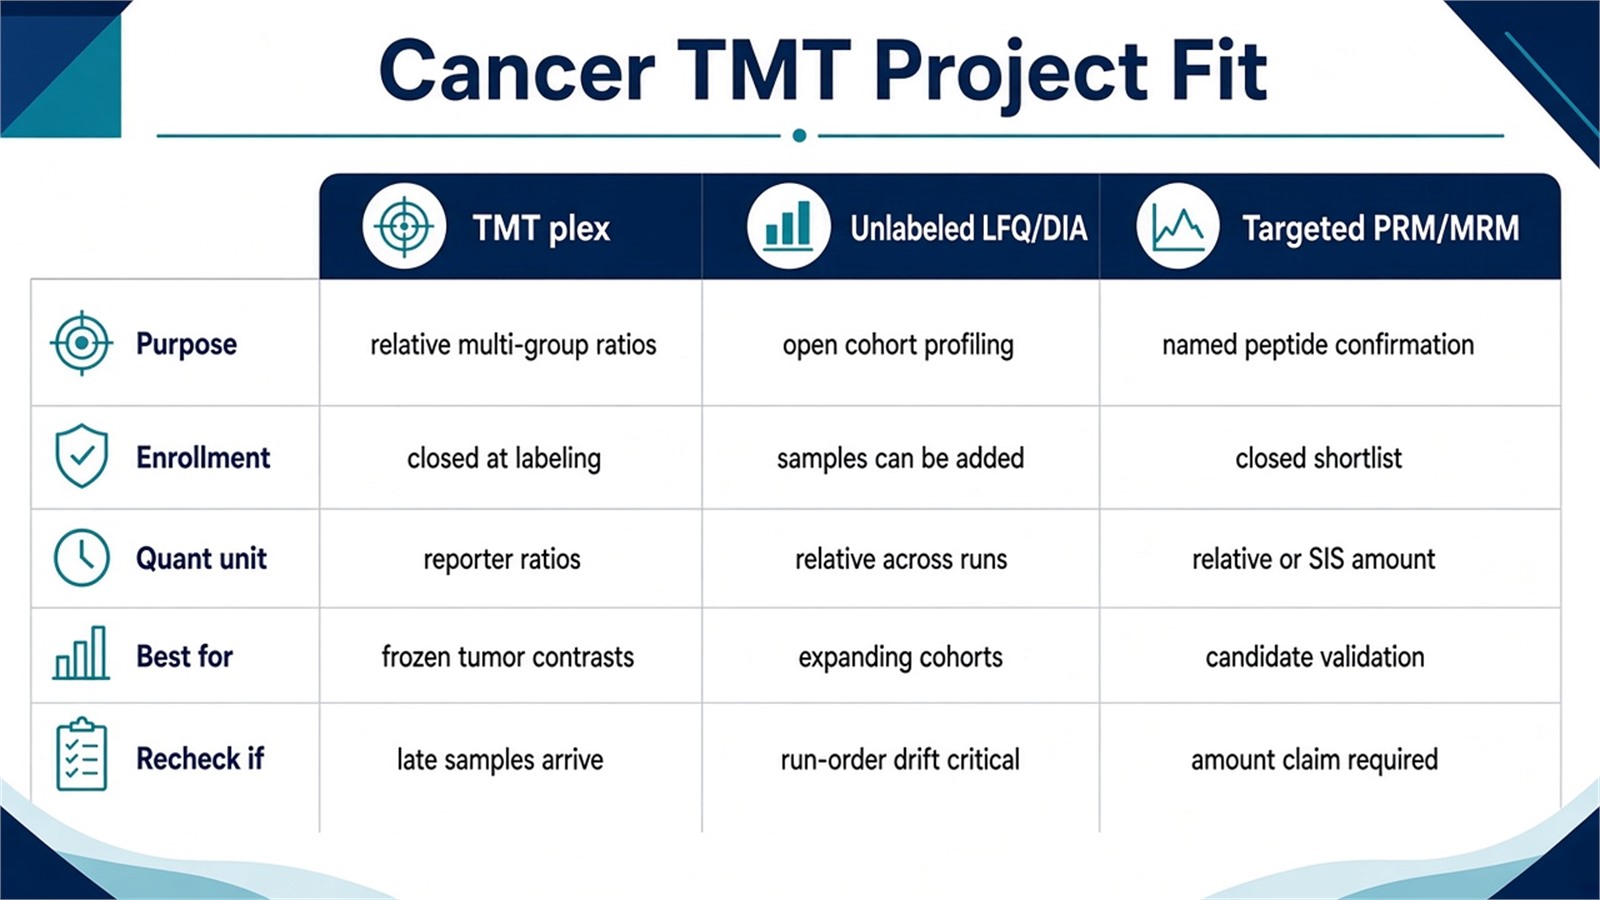
Figure 2. Choose TMT when cancer groups can freeze into one plex; keep unlabeled discovery or targeted confirmation when enrollment or claim unit changes.
TMT more often fits a closed multi-group cancer design that can be labeled together. An exception is a small, well-buffered set that still needs unlabeled flexibility because a follow-up harvest is already booked. Unlabeled DIA or LFQ more often fits open tumor enrollment. An exception is a short closed cohort that must share one injection to limit run-order drift.
Teams with defined cancer groups, matched protein material, and a requested relative contrast can review MtoZ Biolabs TMT Quantitative Proteomics Analysis Service when those fields are declared in the project record.
Frequently Asked Questions
1. Does TMT cancer proteomics diagnose cancer or select therapy?
No. TMT supports relative protein ratios for research contrasts. Diagnostic cutoffs and treatment selection need separate clinical validation beyond the proteomics table.
2. Can TMT replace RNA-Seq for cancer mechanism studies?
No. Transcript and protein layers answer different questions. TMT can compare protein ratios across frozen arms; it does not reproduce transcript abundance units.
3. Must every cancer TMT project use MS3?
No. MS2 can suffice when directional consistency across replicates is enough for triage. MS3 becomes useful when co-isolation is expected to hide a real fold change in complex digests.
4. How should a drug-response cancer study use TMT if more doses will be added later?
Map the doses that exist now onto one plex, or plan a bridge sample for a second plex. If enrollment will stay open, unlabeled acquisition is often simpler.
5. Can TMT cancer results be reported as absolute biomarker concentrations?
No. Reporter ratios are relative. Concentration reporting needs a matched SIS and a declared calibration, usually in a targeted follow-up assay.
MtoZ Biolabs can provide TMT quantitative proteomics for predefined multi-group cancer and related disease-model projects, including plex layout, labeling, LC-MS/MS, and relative matrix reporting when sample type and study design are available.
If further evaluation of channel mapping, bridge design, MS2 versus MS3 readout, or whether unlabeled quantification fits better is needed, project details can be submitted for a feasibility review.
Reference
- A. Thompson, J. Schafer, K. Kuhn, S. Kienle, J. Schwarz, G. Schmidt, T. Neumann, R. Johnstone, A.K. Mohammed, C. Hamon (2003). Tandem mass tags: a novel quantification strategy for comparative analysis of complex protein mixtures by MS/MS. Anal. Chem., 75, 1895-1904. https://doi.org/10.1021/ac0262560
- L. Ting, R. Rad, S.P. Gygi, W. Haas (2011). MS3 eliminates ratio distortion in isobaric multiplexed quantitative proteomics. Nat. Methods, 8, 937-940. https://doi.org/10.1038/nmeth.1714